Some ACA health insurance plans have lots of enrollees, few providers : Shots

Some ACA health insurance plans have lots of enrollees, few providers : Shots

The Affordable Care Act saw a record number of sign ups this year, but some people are having trouble finding doctors in their health plan networks.

Getty Images


hide caption

toggle caption

Getty Images


The Affordable Care Act saw a record number of sign ups this year, but some people are having trouble finding doctors in their health plan networks.

Getty Images

The Affordable Care Act may be struggling with its own success.

Record enrollment over the last two years brought more consumers into the health insurance market. At the same time, many insurers began offering smaller networks of doctors and hospitals, partly to be price competitive.

That combination left some patients scrambling to find an available in-network physician or medical facility. That can be a challenge, especially when enrollees must rely on inaccurate provider lists from their insurance company. A recent federal report found that 243 out of 375 insurance company plans reviewed by regulators failed to meet network standards.

‘The last thing she needed’

Take what happened to a central Pennsylvania policyholder, who in January fell and broke her arm and a bone near her eye.

She was directed by the hospital that provided her emergency care to follow up with an orthopedist, recounted Kelly Althouse, the patient’s insurance agent, who works near Reading, Pa. Althouse’s client spent hours calling orthopedic doctors listed in the provider directory of her new health plan from insurer Ambetter Health, a national carrier that in 2019 started offering ACA plans in Pennsylvania. Several doctors said they weren’t part of the network, despite being listed by the company, Althouse said. It took about 15 tries before her client found an in-network doctor who would see her.

That “was the last thing she needed when she was already feeling terrible,” said Althouse.

It’s a story that has been repeated to her multiple times since January, when the new plan year began. Her clients have “bombarded” her with calls, saying a range of physicians and other providers were not accepting the insurance, even if that provider was listed in the plan’s own directory. “The thing that shocked me was how many offices told my clients, ‘We have never heard of this company,'” Althouse said.

For its part, Ambetter officials said in a written statement to KHN that their network in Pennsylvania “meets or exceeds regulatory standards.”

The size of insurers’ networks of contracted doctors and hospitals, particularly in ACA plans, has long drawn concern. In recent years, insurers have trended toward offering smaller networks, in part to cut costs and keep premiums in check.

Problems arise when patients cannot find local in-network providers and must either pay more, for out-of-network care, if that’s even an option in their plans, or travel farther for in-network care.

It wasn’t supposed to be that way anymore, after new rules kicked in this year to address such issues.

More oversight, but is it enough?

For one, federal regulators are again checking whether insurers have enough providers. That comes after a 2021 court ruling that reversed a Trump administration move to eliminate such federal oversight.

In addition, new “time and distance” standards went into effect, requiring insurers to make available, within certain driving distances, at least one provider for each of a variety of physician specialties. For example, a large metro area must have enough endocrinologists for at least 90 percent of enrollees to be able to find one within 15 miles or a 30-minute drive.

Yet insurance brokers in multiple states told KHN that many clients are having trouble finding in-network providers across a variety of health plans. Even when they do, patients on some plans face “a four- to five-month wait to see a primary care doctor,” said Tracy McMillan, president of Marketplace Insurance Exchange, an insurance brokerage in the Dallas-Fort Worth area.

Under the Affordable Care Act, insurers must “ensure a sufficient choice of providers.” But there is no single nationwide standard on what to measure to determine network adequacy, and both federal and state regulators have authority to oversee the plans.

“These exchange networks have never had much rigorous oversight,” said Karen Pollitz, a senior fellow at KFF.

But access is still limited in some areas and even the standards themselves may not be tough enough, say policy experts and brokers.

“We have insurers that don’t even have a hospital in some counties,” said Lauren Jenkins, owner of Native Oklahoma Insurance, a brokerage based near Tulsa. “How do they even get approved to be in these counties?”

In a metro area no more than 40 miles across, a plan could theoretically have as few as 10 doctors and three facilities in network and still meet these standards, Pollitz said.

In Texas, North Carolina, and other parts of the country, new companies, often charging lower premiums, have entered the ACA market. Some have networks “that are very, very tiny,” said Don Hilke, owner of ClearBenefits Group in Durham, N.C. Even larger carriers are either squeezing their networks to compete on price or enrolling so many customers that they are stretching their existing networks.

‘Everyone in a pickle’

In Texas, two smaller insurance companies left the market, leaving the remaining insurers without enough doctors to absorb the policyholders who had to find other coverage, said Ronnell Nolan, president and CEO of Health Agents for America, a membership association for independent brokers. “It left everyone in a pickle.”

Federal regulators propose more changes for next year, including requiring insurers to meet appointment wait-time standards.

More has been done this year too, including reviewing insurer networks, said Ellen Montz, deputy administrator and director of the federal Center for Consumer Information and Insurance Oversight, part of the Centers for Medicare & Medicaid Services.

Insurers pegged as having a shortfall in their networks must now report monthly to CMS their “good faith efforts to fill those gaps” and how many complaints they get from consumers about access, she wrote.

Montz did not say how many insurers have fallen short, but the December report from the U.S. Government Accountability Office noted that CMS found the majority of insurance companies whose medical or dental plans were reviewed by federal regulators in August failed to meet network adequacy standards. CMS told the GAO that all plans eventually satisfied the requirements or provided “an acceptable justification as to why they were unable to meet the standards.”

Creating networks and keeping lists of participating providers up to date pose ongoing challenges, said Jeanette Thornton, executive vice president of policy and strategy at AHIP, the health insurance industry’s leading lobbying group. Those include the need to rely on providers to inform insurers when they move, retire, or stop accepting new patients.

Questions about the accuracy of provider directories persist. Dr. Neel Butala, an assistant professor at the University of Colorado School of Medicine, found that fewer than 20{515baef3fee8ea94d67a98a2b336e0215adf67d225b0e21a4f5c9b13e8fbd502} of more than 449,000 physician listings had consistent address and specialty area information across five large insurers’ directories, according to a research letter published in the Journal of the American Medical Association on March 14.

A lawsuit filed in August 2022 in the U.S. District Court for the Northern District of Illinois alleges the provider networks for Centene’s Ambetter plans “are simply false and are often just copies of physician directories from other sources.”

Without accurate directories, the lawsuit alleges, patients face “delays in treatment, inability to get treatment, traveling to see an in-network provider who is hundreds of miles away, and paying out-of-pocket for out-of-network providers.” Similar allegations are included in ongoing lawsuits first filed in 2021 by the San Diego City Attorney against three California insurers.

The “No Surprises Act,” which went into effect more than a year ago, requires insurers to update their provider directories every 90 days. No insurers have yet been penalized for failing to update theirs, said CMS’s Montz. The law also stipulates that if patients get hit with an out-of-network charge because they relied on inaccurate information, the insurer can charge the patient only the in-network rate.

In October, CMS published an official query asking for comment on whether the federal government should create its own national database of in-network medical providers, an inquiry that drew hundreds of responses, both for and against.

There has been no indication whether such a plan will move forward.

KHN (Kaiser Health News) is a national newsroom that produces in-depth journalism about health issues. Together with Policy Analysis and Polling, KHN is one of the three major operating programs at KFF (Kaiser Family Foundation). KFF is an endowed nonprofit organization providing information on health issues to the nation.

Blood pressure checks to fight Black maternal mortality : Shots

Blood pressure checks to fight Black maternal mortality : Shots

Kennise Nevers holds her son, AJ, in her arms at household. Nevers’ mother, Nancy Josey, seems on.

Jesse Costa/WBUR


hide caption

toggle caption

Jesse Costa/WBUR


Kennise Nevers retains her son, AJ, in her arms at dwelling. Nevers’ mother, Nancy Josey, appears to be like on.

Jesse Costa/WBUR

With each feet flat on the flooring, Kennise Nevers settles into the couch in her residing home. She peels open up a blood stress cuff, and straps it around her left arm, exhaling as it squeezes her bicep.

Soon after a moment, she receives the reading through. “It is really fantastic,” says the mother of two from Brockton, Massachusetts.

Nevers, 37, tracked her blood force at home just about every working day for months as component of a plan for clients at Boston Health-related Middle who are pregnant or just lately experienced infants and are at hazard for hypertension. That best examining Nevers acquired was transmitted to her health care file and reviewed by a nurse.

Blood force is just just one way to evaluate a person’s well being, but all through being pregnant and quickly soon after, it can be a essential metric. Unchecked, superior blood tension can contribute to serious complications for the expecting female and little one, and increase the possibility of demise.

So for Nevers, it was a reduction to know that wellness treatment suppliers have been monitoring her quantities so carefully.

“Of program, you might be generally going to get worried: It truly is being pregnant. Issues improve all the time,” she states. “But it eased some of my worry. I experience like I had physicians often on my aspect, searching after me. I was not forgot about.”

Being pregnant-relevant loss of life

Scientific tests show that Black folks are far more than two times as likely as white men and women to knowledge significant being pregnant-similar difficulties, and practically 3 situations as probably to have a being pregnant-connected demise.

The U.S. has the worst maternal mortality price of superior-money nations around the world in the world — and the figures are climbing. New federal information demonstrates maternal deaths spiked 40{515baef3fee8ea94d67a98a2b336e0215adf67d225b0e21a4f5c9b13e8fbd502} in 2021.

Several significant challenges stem from higher blood stress, claims Dr. Tina Yarrington, director of maternal-fetal medicine at BMC.

“It is the root bring about for a lot of, several maternal wellbeing inequities,” she suggests. “People today who are marginalized by structural racism, individuals who are Black, African American, Latina, Hispanic, undergo bigger levels of hypertension and bigger concentrations of complications when that hypertension strikes.”

Blood pressure measures the power of blood pushing towards the artery partitions. When that drive is far too large through pregnancy — a issue named pre-eclampsia — it can lead to stroke, organ problems, pregnancy loss or small birth pounds for the child. It also raises the risk of death for the pregnant person and newborn.

Pre-eclampsia impacts about 14{515baef3fee8ea94d67a98a2b336e0215adf67d225b0e21a4f5c9b13e8fbd502} of BMC’s white sufferers, but 18{515baef3fee8ea94d67a98a2b336e0215adf67d225b0e21a4f5c9b13e8fbd502} of its Black clients — a compact but significant change.

“That is the gasoline for this hearth,” Yarrington states. “That is why we’re putting so much power and get the job done into pre-eclampsia, in the fascination of not just better outcomes, but much better results precisely for the populations that have experienced from inequities.”

Near enjoy, quick action

Higher blood stress is at times referred to as the “silent killer” since it can out of the blue increase to unsafe ranges without having causing agony or other indicators. That is why BMC has assigned a nurse, Megan O’Brien, to check out patients’ quantities everyday.

Every time a patient will take a examining at house, their blood pressure cuff sends the quantities straight to their electronic health file. The cuffs do not want an world-wide-web connection they use the sign of close by cell towers.

“The to start with factor I do each individual morning is search at all of the high readings that have arrive in considering that the evening before,” O’Brien says.

If she sees a about number, she follows up ideal absent — normally with the enable of interpreters for sufferers who don’t speak English.

The patient might require a new treatment. Or they may need to have to arrive to the healthcare facility to be monitored. In some cases, blood pressure spikes so rapidly that sufferers have to deliver their toddlers early to avoid serious complications.

After delivery, some sufferers are even now at hazard of establishing seizures, stroke, heart assaults or other issues. O’Brien displays their numbers, as well.

The every day at-house blood force checks enable nurses and doctors to spot troubles early and act sooner. “We are intervening so much more quickly in these possible problems that could be taking place at household,” O’Brien claims. “It truly is seriously about catching people as speedy as feasible.”

A mobile blood pressure monitoring procedure in its packaging. The check sends the details from every reading through right to Boston Clinical Centre for wellbeing employees to evaluation.

Jesse Costa/WBUR


conceal caption

toggle caption

Jesse Costa/WBUR


A cellular blood strain monitoring process in its packaging. The keep track of sends the knowledge from each and every reading immediately to Boston Healthcare Centre for health and fitness workers to overview.

Jesse Costa/WBUR

BMC’s property-checking method began for the duration of the COVID pandemic. The hospital started providing blood force cuffs to postpartum clients in 2020, when in-man or woman health-related visits were being disrupted, and last spring, expanded to include expecting sufferers.

‘Interrogate’ disparities

This hard work is section of a sweeping healthcare facility-wide initiative to just take superior treatment of men and women of shade and remove racial and ethnic disparities in overall health treatment.

Healthcare facility leaders dove into facts about their patients and uncovered stark disparities in being pregnant, as nicely as COVID, diabetic issues, cancer and behavioral wellbeing. They found, for example, that their Black clients had been 2 times as likely to develop being pregnant-associated troubles as white patients.

“You will find no way you can discover all those factors and not interrogate them and have an intentionality to improve them,” suggests Dr. Thea James, vice president of mission and co-executive director of the Wellbeing Equity Accelerator. “It is unethical to see people matters and leave them there.”

Some of the perform is in getting rid of the likely for bias and subjectivity throughout final decision-building — for instance, deciding when pregnant patients with pre-eclampsia must provide their babies.

“We noticed that it was taking two times as prolonged to make that final decision in Black females,” James says. “So the to start with point we did was to standardize the conclusion-generating course of action.”

BMC has enrolled hundreds of individuals in the initiative to keep track of blood force at residence throughout and soon after pregnancy about 80{515baef3fee8ea94d67a98a2b336e0215adf67d225b0e21a4f5c9b13e8fbd502} of them are Black or Hispanic, reflecting the makeup of the hospital’s overall affected person populace.

Basic, but not simple

It may perhaps look like a very simple intervention. But not all overall health care companies have funding to pay back for a residence-checking software and committed personnel to operate it. Well being insurance policy ideas ordinarily do not deal with these fees.

And though some individuals really don’t intellect examining their blood force at house, other individuals may come across it too stress filled or time-consuming.

“Making a routine is tricky for everything,” says Dr. Lara Kovell, director of the pregnancy and heart disease clinic at UMass Memorial Health care Heart in Worcester, Mass.

Kovell is element of a staff of researchers at UMass Memorial, Yale University and the College at Buffalo who are studying the use of at-home support, such as blood tension monitoring, for postpartum patients.

“Maternal mortality remaining three- to 4-fold larger in our Black ladies is just one thing that genuinely desires to transform,” Kovell claims. “And I consider hypertension is a single of the points that will get to that.”

Dr. Rose Molina, an OB-GYN at Beth Israel Deaconess Clinical Heart in Boston, reported analysis on house monitoring so far continues to be inconclusive — while there appears to be minor downside to providing people blood strain cuffs at household.

“I do not imagine that there is automatically harm,” she states, “but there is certainly still questions close to how do we develop the process close to self-monitoring that genuinely is substantial-benefit in conditions of acquiring a scientific effect, and also saving expenses, ideally, in some way.”

Health professionals at BMC are continue to learning the impacts of dwelling monitoring, but they have viewed some promising early success.

Infant AJ’s arrival

Kennise Nevers was eight months pregnant and cooking rooster for a major relatives dinner a person evening in October when her blood force instantly spiked.

“We were actually acquiring ready to enjoy playing cards,” Nevers recollects. “And I was like, ‘Oh, permit me just verify my blood pressure just before I engage in.’ And the evening ended fairly fast.”

She went to the healthcare facility suitable absent. The next working day, medical doctors induced labor, and her infant, AJ, was born.

He arrived 3 months early, but solid and nutritious.

“It was a relief,” Nevers claimed. “I was so fearful in the course of the pregnancy due to the fact of my blood strain.”

Nevers produced it past the high-risk postpartum times with no producing a complication.

But she has long-term hypertension, so she continue to retains a blood strain cuff close by.

Scientists warned a decade ago American lives were shortening. Then it got worse : Shots

Scientists warned a decade ago American lives were shortening. Then it got worse : Shots

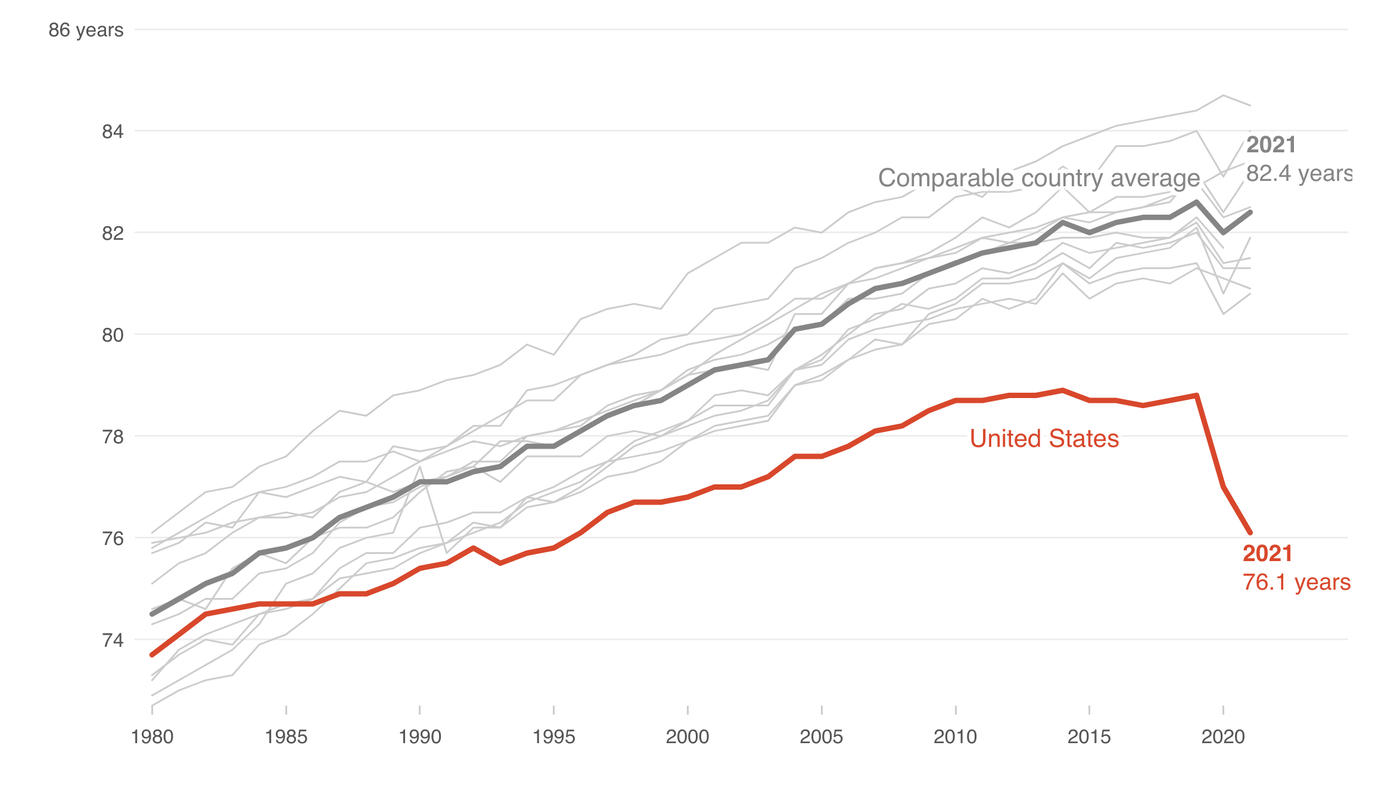
Just before Christmas, federal health officials confirmed life expectancy in America had dropped for a nearly unprecedented second year in a row – down to 76 years. While countries all over the world saw life expectancy rebound during the second year of the pandemic after the arrival of vaccines, the U.S. did not.

Then, last week, more bad news: Maternal mortality in the U.S. reached a high in 2021. Also, a paper in the Journal of the American Medical Association found rising mortality rates among U.S. children and adolescents.

“This is the first time in my career that I’ve ever seen [an increase in pediatric mortality] – it’s always been declining in the United States for as long as I can remember,” says the JAMA paper’s lead author Steven Woolf, director emeritus of the Center on Society and Health at Virginia Commonwealth University. “Now, it’s increasing at a magnitude that has not occurred at least for half a century.”

Across the lifespan, and across every demographic group, Americans die at younger ages than their counterparts in other wealthy nations.

How could this happen? In a country that prides itself on scientific excellence and innovation, and spends an incredible amount of money on health care, the population keeps dying at younger and younger ages.

An unheard alarm

One group of people are not surprised at all: Woolf and the other researchers involved in a landmark, 400-page study ten years ago with a name that says it all: “Shorter Lives, Poorer Health.” The research by a panel convened by the National Academy of Sciences and funded by the National Institutes of Health compared U.S. health and death with other developed countries. The results showed – convincingly – that the U.S. was stalling on health advances in the population while other countries raced ahead.

The authors tried to sound an alarm, but found few in the public or government or private sectors were willing to listen. In the years since, the trends have worsened. American life expectancy is lower than that of Cuba, Lebanon, and Chechnya.

Ten years later, here’s a look back at what that eye-popping study found, and why the researchers involved believe it’s not too late to turn the trends around.

Beyond bad habits

Americans are used to hearing about how their poor diets and sedentary lifestyles make their health bad. It can seem easy to brush that off as another scold about eating more vegetables and getting more exercise. But the picture painted in the “Shorter Lives” report could shock even those who feel like they know the story.

“American children are less likely to live to age 5 than children in other high-income countries,” the authors write on the second page. It goes on: “Even Americans with healthy behaviors, for example, those who are not obese or do not smoke, appear to have higher disease rates than their peers in other countries.”

The researchers catalog what they call the “U.S. health disadvantage” – the fact that living in America is worse for your health and makes you more likely to die younger than if you lived in another rich country like the U.K., Switzerland or Japan.

“We went into this with an open mind as to why it is that the U.S. had a shorter life expectancy than people in other countries,” says Woolf, who chaired the committee that produced the report. After looking across different age and racial and economic and geographic groups, he says, “what we found was that this problem existed in almost every category we looked at.”

That’s why, says Eileen Crimmins, professor of gerontology at the University of Southern California who was also on the panel that produced the report, they made a deliberate choice to focus on the health of the U.S. population as a whole.

“That was a decision – not to emphasize the differences in our population, because there is data that actually shows that even the top proportion of the U.S. population does worse than the top proportion of other populations,” she explains. “We were trying to just say – look, this is an American problem.”

Digging into the ‘why’

The researchers were charged with documenting how Americans have more diseases and die younger and to explore the reasons why.

“We were very systematic and thorough about how we thought about this,” says Woolf. The panel looked at American life and death in terms of the public health and medical care system, individual behaviors like diet and tobacco use, social factors like poverty and inequality, the physical environment, and public policies and values. “In every one of those five buckets, we found problems that distinguish the United States from other countries.”

Yes, Americans eat more calories and lack universal access to health care. But there’s also higher child poverty, racial segregation, social isolation, and more. Even the way cities are designed makes access to good food more difficult.

A fruit seller at Dom Pedro market in Coimbra, central Portugal. A lack of access to fresh fruits and vegetables in the U.S. may contribute to Americans shorter lifespan.

PATRICIA DE MELO MOREIRA/AFP via Getty Images


hide caption

toggle caption

PATRICIA DE MELO MOREIRA/AFP via Getty Images


A fruit seller at Dom Pedro market in Coimbra, central Portugal. A lack of access to fresh fruits and vegetables in the U.S. may contribute to Americans shorter lifespan.

PATRICIA DE MELO MOREIRA/AFP via Getty Images

“Everybody has a pet thing they worry about and say, ‘it’s oral health’ or ‘it’s suicides’ – everyone has something that they’re legitimately interested in and want to see more attention to,” says John Haaga, who was the director of the Division of Behavioral and Social Research at the National Institute on Aging at NIH, before he retired. “The great value of an exercise like this one was to step back and say, ‘OK, all of these things are going on, but which of them best account for these long-term population level trends that we’re seeing?’ “

The answer is varied. A big part of the difference between life and death in the U.S. and its peer countries is people dying or being killed before age 50. The “Shorter Lives” report specifically points to factors like teen pregnancy, drug overdoses, HIV, fatal car crashes, injuries, and violence.

“Two years difference in life expectancy probably comes from the fact that firearms are so available in the United States,” Crimmins says. “There’s the opioid epidemic, which is clearly ours – that was our drug companies and other countries didn’t have that because those drugs were more controlled. Some of the difference comes from the fact that we are more likely to drive more miles. We have more cars,” and ultimately, more fatal crashes.

“When we were doing it, we were joking we should call it ‘Live free and die,’ based on the New Hampshire slogan, [‘Live free or die’],” Crimmins says. “The National Academy of Sciences said, ‘That’s outrageous, that’s too provocative.’ “

There are some things Americans get right, according to the “Shorter Lives” report: “The United States has higher survival after age 75 than do peer countries, and it has higher rates of cancer screening and survival, better control of blood pressure and cholesterol levels, lower stroke mortality, lower rates of current smoking, and higher average household income.” But those achievements, it’s clear, aren’t enough to offset the other problems that befall many Americans at younger ages.

All of this costs the country tremendously. Not only do families lose loved ones too soon, but having a sicker population costs the country as much as $100 billion every year in extra health care costs.

“Behind the statistics detailed in this report are the faces of young people – infants, children, and adolescents – who are unwell and dying early because conditions in this country are not as favorable as those in other countries,” the paper’s authors wrote.

Little action, despite the stakes

“Shorter Lives” is filled with recommended next steps for the government, especially the NIH, which has a budget of more than $40 billion annually to conduct research to improve Americans’ health.

The NIH should undertake a “thorough examination of the policies and approaches that countries with better health outcomes have found useful and that may have application, with adaptations, in the United States,” the authors wrote.

In other words: let’s figure out what they are doing that works in other places, and do it over here.

Dr. Ravi Sawhney, who helped conceive of and launch the “Shorter Lives” study at NIH before he left the agency, had high hopes that the report would make a mark. “I really thought that when the results came out, they would be so obvious that people would say: Let’s finally do this,” he says.

Ten years on, how much of the detailed action plan has been done?

“To be brief, very little of that happened,” Woolf says. At the time, he says, NIH officials didn’t seem very interested in raising awareness about the panel’s findings or in following up on its proposed research agenda. “There was some media coverage at the time that the report rolled out, but NIH was not involved in trying to promote awareness about the report.”

Crimmins agrees. “There was a little bit more research, but there wasn’t any policy reaction,” she says. “I thought there might be, because it’s embarrassing, but it just tends to be ignored.” Those who are interested in this issue, she notes, tend to be those invested in “marvelous things they think are going to delay aging,” even though people older than 75 are the only age group in the country that already does comparatively well.

Haaga, the former NIH division director, also thinks the response at the agency was lacking. “Not nearly enough has been done, given the stakes and given what we could learn,” he says.

In response to NPR’s request for comment for this story, NIH pointed to a subsequent panel on midlife mortality, several initiatives the agency has undertaken on disparities between subgroups within the U.S., and a recent paper funded by NIH that looked again at international life expectancy.

Outgoing NIH Director Francis Collins told NPR in 2021 that it bothered him that there hadn’t been more gains to American life expectancy during his tenure. In his view, the success of NIH in achieving scientific breakthroughs hadn’t translated to more gains because of problems in society that the research agency had little power to change.

Woolf calls it a misconception to assume that America’s great scientific minds and medical discoveries translate to progress for the health of the population. “We are actually very innovative in making these kinds of breakthroughs, but we do very poorly in providing them to our population,” he says.

‘We can’t touch everything’

Department of Health and Human Services Secretary Xavier Becerra answered NPR’s question at a press conference earlier this month about work the agency was doing to address lagging life expectancy by mentioning COVID-19 and vaccine hesitancy, along with mental health issues and gun violence.

“There’s so many things that we’re doing,” Becerra said. “We can’t touch everything. We can’t touch state laws that allow an individual to buy an assault weapon and then kill so many people. We can only come in afterwards.”

Secretary of the Department of Health and Human Services Xavier Becerra at a news conference at HHS headquarters in Washington, DC on March 9, 2023. Becerra said gun violence contributes to shorter lifespans in the U.S.

Drew Angerer/Getty Images


hide caption

toggle caption

Drew Angerer/Getty Images


Secretary of the Department of Health and Human Services Xavier Becerra at a news conference at HHS headquarters in Washington, DC on March 9, 2023. Becerra said gun violence contributes to shorter lifespans in the U.S.

Drew Angerer/Getty Images

CDC Director Rochelle Walensky responded by listing some of the agency’s work on mental health and vaccines, and acting NIH director Larry Tabak pointed to research on health disparities.

HHS did not answer a follow up question about whether the agency has considered a national commission or similar effort to address American life expectancy and poor health.

Sawhney thinks the federal government should try harder to fix the problems documented in the “Shorter Lives” report. He doesn’t think lack of public awareness is the problem. “I really think that most Americans know that Americans are more overweight and obese and that we have higher rates of disease and live shorter lives than other countries,” he says, “It’s just the NIH and the CDC that don’t want to take the responsibility for that failure or to do anything about it.”

Crimmins says, in her experience, lawmakers and federal health officials don’t like talking about how the U.S. is lagging behind other countries.

“I convened a meeting in Washington with the National Center for Health Statistics [part of CDC] about increasing healthy life expectancy,” she recalls. “It was a relatively small meeting, but we brought experts from Canada.” An official at the time gave what she calls a “typical” response, saying: “Oh, we can’t have anything but an American solution to these issues – we can’t listen to other countries.”

“International studies are not the flavor of the month – they never will be,” says Haaga. “The problem with foreign countries is that they’re not in someone’s congressional district.”

It’s more than a missed opportunity, says Woolf. It’s a tragedy.

“If you add up the excess deaths that have occurred in the United States because of this unfolding problem, it dwarfs what happened during COVID-19, as horrible as COVID-19 was,” Woolf says. “We’ve lost many more Americans cumulatively because of this longer systemic issue. And if the systemic issue is unaddressed, it will continue to claim lives going forward.”

Small victories are possible

Taking stock of the many ways in which Americans are sicker and die younger can be overwhelming, says Haaga. “It’s such a long list, that might partly be why the issue doesn’t grab people,” he says. “They just go, ‘Oh, my gosh, that’s depressing, what’s on the other channel?’ But there’s a lot of things that could be done, and small victories are victories.”

According to the “Shorter Lives” report, “the important point about the U.S. health disadvantage is not that the United States is losing a competition with other countries, but that Americans are dying and suffering at rates that are demonstrably unnecessary.”

Rather than feel overwhelmed at the immensity of the problems, Sawhney suggests, the focus should instead be on the fact that every other rich country has been able to figure out how to help people live longer, healthier lives. That means that Americans could do it too, he says.

He believes that the changes might not be as hard as some policymakers and health officials seem to think. “You look at these healthier countries, they’re free countries – England, France, Italy – they’re not banning delicious foods. They’re not chaining people to treadmills,” he says. “Americans love to travel to Europe, to Australia, to Canada to enjoy their foods and their lifestyles, and so the idea that we might say, ‘Hey, maybe we could bring some of those lifestyles back’ – I don’t think people are going to go up in arms that we’re taking away their freedoms.”

Getting policy ideas from other countries is just an obvious move, Woolf adds. “If a martian came down to earth and saw this situation, it would be very intuitive that you [would] look at other countries that have been able to solve this problem and apply the lessons learned,” he says.

In historical research he’s been doing, “I found that there are dozens and dozens of countries on almost every continent of the world that have outperformed the United States for 50 years,” he says. “It’s worth taking a look at what they’ve done and Americanizing it – you don’t have to take it right off the shelf.”

Some of the policies he’s identified as helpful include universal, better coordinated health care, strong health and safety protections, broad access to education, and more investments to help kids get off to a healthy start. These policies are “paying off for them,” he says, and could for Americans, too.

Graphic by Ashley Ahn; Edited by Diane Webber

Medical residents unionize at hospitals around the country : Shots

Medical residents unionize at hospitals around the country : Shots

Dr. Leah Rethy is an internal medicine resident with Penn Medicine.

Kimberly Paynter/WHYY


hide caption

toggle caption

Kimberly Paynter/WHYY


Dr. Leah Rethy is an internal medicine resident with Penn Medicine.

Kimberly Paynter/WHYY

Dr. Leah Rethy was pregnant during the first year of her internal medicine residency at the Hospital of the University of Pennsylvania in Philadelphia. She gave birth during her second year. She worked through her 40th week of pregnancy so she could save her time off and spend more time with her newborn.

Now she’s back at work and needs child care. A lot of child care. Medical residents often work long and irregular hours, sometimes as many as 80 hours a week. And child care is one of the main issues motivating Rethy to push for a union at her hospital.

In February, most residents at two major Penn Medicine hospitals decided to form a union, and the National Labor Relations Board will conduct their election in early May. They join a wave of other residents unionizing at programs around the country, most recently at Montefiore hospital in New York, George Washington University in Washington, DC, and Mass General Brigham in Boston.

If successful, these residents would join the Committee of Interns and Residents, the union for medical residents. According to the union’s figures, the number of campaigns spiked from two in 2021, to eight in 2022, an unprecedented increase.

Child care challenges

Rethy says her problem with child care is not unusual — residency follows undergraduate education, and usually four years of medical school, so it overlaps with childbearing years for most people.

“I know a lot of people who’ve delayed having children,” she says. “And I also have heard a number of stories of people delaying having children and then, ultimately, having real challenges getting pregnant because of being older and various factors.”

Dr. Leah Rethy, an internal medicine resident with Penn Medicine, holds her 17 month-old son, Peter.

Kimberly Paynter/WHYY


hide caption

toggle caption

Kimberly Paynter/WHYY


Dr. Leah Rethy, an internal medicine resident with Penn Medicine, holds her 17 month-old son, Peter.

Kimberly Paynter/WHYY

Rethy laments the waiting lists for child care affiliated with Penn Medicine, and says finding her own child care is prohibitively expensive.

“The cost of day care … in a month is about half of my salary in total, and the cost of a nanny is essentially the entirety of my salary,” says Rethy.

She says this experience led her to believe unionizing is the best way for residents to demand better working conditions and higher pay, which would lead to better patient care.

A workforce that can’t leave

Sunyata Altenor is the communications director of Committee of Interns and Residents, or CIR, as the union is known. She says residents who want to unionize understand the program is supposed to be hard work, with long hours. But they want to be treated fairly for their efforts, at a workplace they cannot just choose to leave, as it’s a required part of their training.

“It’s easy to exploit physicians during this time in their career,” Altenor says. “They’re only going to be there for a few years. It’s sort of expected that you go through this hard, hazing culture, and then you come out at the other end an attending physician.”

Prominently, Stanford Medicine did not include residents in their COVID-19 vaccination plans in 2020, leading to protests, and later, a successful unionization drive.

Dr. Chantal Tapé, a third-year resident in family medicine at Penn Medicine, said residents expect challenging work and long shifts, but they would also like to be able to be healthy and financially stable so they can focus on taking care of patients.

She said it is “frustrating as someone who is a prenatal care provider,” to watch colleagues struggle during pregnancy make it to prenatal care appointments and during early parenthood to afford child care. Her colleagues can’t follow advice she recommends for her patients.

Parking, mice and roaches, too

Penn Medicine residents cite many issues for their decision to form a union, such as: the upcoming loss of parking benefits that would lead to an extra $200 monthly cost for residents; and dirty call rooms, which are rooms where residents stay and rest if they have to work overnight.

Residents say some current call rooms have mice and cockroaches.

Dr. Madison Sharp, a third-year OB-GYN resident, recalls not even having a call room to sleep in during a 24-hour rotation.

“So I tried to sleep in a dialysis chair that didn’t lie flat in a conference room off to the side,” she said. “Two years later, residents on that same rotation still don’t have a place to sleep for a few hours on a 24-hour call shift … keep in mind that Penn just opened a billion-dollar hospital but neglected to create physical space for us.”

Medical residents at Penn Medicine say cockroaches and mice have been seen in the “call rooms” where doctors rest during 24-hour shifts.

Resident at Penn Medicine


hide caption

toggle caption

Resident at Penn Medicine


Medical residents at Penn Medicine say cockroaches and mice have been seen in the “call rooms” where doctors rest during 24-hour shifts.

Resident at Penn Medicine

In a prepared statement, Penn Medicine says it values residents and is “proud of the ways in which we have sought to continually improve resident life and wellness.” The statement maintains it provides benefits and increased salaries to offer competitive working conditions. Starting July 1, resident salaries will start at a little more than $69,000 a year, according to Penn Medicine. They also say “trainees” should bring their concerns to administrators through an existing advisory council.

“I was the president of this council last year, and I can tell you firsthand that the House staff governing council is extremely limited in what we could accomplish,” Sharp said. “It was incredibly frustrating to advocate for residents and fellows and not be heard or have our concerns brushed aside or dismissed.”

Residents at the University of Vermont Medical Center voted to form a union last year. Following the successful union vote for residents, support staff including maintenance workers and technicians are unionizing as well.

The union for residents at Jersey City Medical Center has already argued for a better work environment in the years since they’ve organized, said Dr. Andrea Attenasio, a fourth-year resident in orthopedic surgery. For instance, she said they recently managed to ask the hospital to provide food for residents who work after hours; to provide bedsheets for the rooms where residents stay if they work overnight; and to stop tying salary increases for residents to overall hospital performance, a major concern with rising inflation and cost of living.

Attenasio said the bargaining power and strength in numbers that comes from being a union member makes a difference for residents:.

“It’s an automatic support system and it allows you to go to your hospital administration as a united front.”

‘The People’s Hospital’ doctor treats Houston’s uninsured and undocumented : Shots

‘The People’s Hospital’ doctor treats Houston’s uninsured and undocumented : Shots

Paramedics at Ben Taub General Hospital speed a patient with a gunshot wound to the trauma team for further care. Ben Taub is the largest safety-net hospital in Houston.

Gregory Smith/Corbis via Getty Images


hide caption

toggle caption

Gregory Smith/Corbis via Getty Images


Paramedics at Ben Taub General Hospital speed a patient with a gunshot wound to the trauma team for further care. Ben Taub is the largest safety-net hospital in Houston.

Gregory Smith/Corbis via Getty Images

As a doctor in a so-called “safety-net” hospital, Ricardo Nuila’s daily practice looks quite different from that of his colleagues who work in private or not-for-profit hospitals. That’s because safety-net hospitals treat everyone who walks in the doors — regardless of insurance status.

Many of Nuila’s patients at Houston’s Ben Taub Hospital are dealing with serious illnesses as a result of not being able to get access to basic preventive care. “What we see is that patients’ lack of health care has meant that the disease has been able to grow within their bodies,” he says. “Their cancer is widespread, or we find that they have an infection that has not been treated or discovered.”

In his new book, The People’s Hospital, Nuila writes about his experiences at Ben Taub, which is the largest safety-net hospital in Houston. He says despite the hospital’s budget constraints, the doctors and nurses there still manage to provide quality health care. By limiting the number of patients a practitioner can see in a day, Ben Taub allows physicians to spend more time with their patients than is typical.

“My cap is 15 patients in one day,” Nuila says. “That’s compared to some of my colleagues in the private world, who I’ve heard admit up to 24 patients in one night, or don’t carry a cap.”

Because resources are tight at Ben Taub, there is an emphasis on using them mindfully, Nuila says. Instead of ordering an MRI with the push of a button, for instance, he might talk to the radiologist directly, to find out if extra imaging is really called for. “There are benefits to further discussion between medical professionals about emergencies and how to deal with these emergencies,” he says.

Overall, Nuila says, working at a safety-net hospital allows him to keep his focus on medicine: “I like that I have the time to be able to hear my patients’ stories, that I don’t have to think about billing all the time, that I can sit with them and hear about why they came to the hospital and learn about their lives — and that, no matter what, we are going to be thinking about how best to help them, regardless of whether they have insurance or not.”

Interview highlights

The People's Hospital, by Ricardo Nuila

On treating undocumented people at the hospital

It’s not considered illegal. … The law EMTALA — the Emergency Medical Treatment & Labor Act — that was passed in the 1980s, that states that anybody in the United States, whether you’re a resident or not, whether you have health insurance or not, can go to a hospital and receive an exam and stabilizing treatment. So that’s a right that everybody in the United States has, regardless of citizenship. What’s different about the safety-net hospital is that we have clinics and we have chronic care also — and that was under question by certain politicians, who ultimately found that it didn’t make any sense to question that. Because when you get in the way of preventive care, when you get in the way of primary care, those patients end up coming to the emergency room and they become much more expensive. … So, [the politicians] decided that the financial gains were more important [than limiting care].

On explaining the American health care system to uninsured patients

The patients are all so different — some have had multiple family members in the United States before, so they understand the landscape a little bit better. But yeah, it can feel very, very contradictory when I tell patients that, well, “You need health insurance for that.” And they will say sometimes, “Well, in Mexico or in Guatemala (or whatever), I don’t necessarily.” And it’s hard to explain that in the richest country in the world, there’s little available for people without health care insurance.

Now, I’m happy that in Harris County [in Texas], where I work at Harris Health, we can provide a robust set of services. But somebody who lives outside of the county doesn’t have availability for those services. And that’s one of the things that I’ve argued, is that the line between Mexico and the United States is not as important as the line between Harris County and Fort Bend County, for instance, in some of the treatments that we give to patients.

On speaking Spanish with patients

That’s one of the reasons that I love my job and I love the hospital where I work — I can speak Spanish. … The people are so happy to hear somebody attempt to speak their language, and not just on a translation basis, but the flavor of the language and also thinking about the locations [they come from]. For instance, when I ask somebody where they’re from and they say Mexico or El Salvador, it’s never enough for me to hear just a country. I need to ask a region so I can situate it in my mind, the map, and draw a relationship that I have with that region. And so I think it helps a lot for building trust with patients.

On his reaction when very sick patients put their faith in God

I don’t dismiss it. Because I feel that science and medicine, we don’t know everything. There’s a lot of mystery in this world and I think faith is important. I’m not saying that faith in one particular religion is important, but faithfulness is important. I think that in my experience, when people demonstrate faith, whether it’s in their God or whether it’s in the treatment, they do better. It’s not my job to take away that person’s faith. What I tell people is that I’m just doing my job, which is [that] I’m a human being, and I need to tell you … the recommendation from doctor human beings for this illness and for the treatment, but that I’m just a person and I don’t know. And that’s the truth – we don’t know everything. We have very good ideas. When somebody is close to death, we can prognosticate quite accurately if that person’s going to die or not. But I can not tell exactly when that is going to happen. And I don’t want to rob somebody of their faithfulness.

On struggling with thoughts of suicide after the suicide of a friend and colleague

I think everything was a struggle. And I think that seeing somebody like Dave, who I admired so much, who was a friend, my best friend in the hospital, who I could speak with and who was so knowledgeable and intelligent — just to know that that is a risk for me as I grow older. Dave was also a very good father and it’s something that I’ve struggled with, parenting.

It felt so much like a pressure of trying to be a good father while trying to be a good doctor, while trying to be a good writer. They can work together, but there are moments where they feel like they can just implode on themselves. And I think that knowing that that had happened to my friend weighed on me and made me think, Is this going to be me? Is this the fate that so many of us who care a lot that we face? …

Therapy helped. I found a therapist who was very attuned to people who were creative types. … That listening really helped. My relationships improved. When I was at my lowest, I could look at my relationships with the people who were around me, who I valued the most, and I can see that at that moment they weren’t great relationships. And somehow over time, those relationships started to improve and that helped immensely. I think that writing also helped me too, at the end of the day.

On hospital staff losing their sense of meaning with their job because of burnout

For me that just demonstrates a real fundamental problem with how health care is administered in this country. If something like medicine, where you are helping people on a daily basis, if you can’t see the meaning behind that, that’s a bad omen. Whenever a patient tells me, “I’m thirsty” and I go get them ice water, I feel really good that day. Something as simple as that. With my Spanish-speaking patients, they can say one phrase to me and I will feel satisfied for that day — when they say, “Que amable,” which means you were very kind in the way you said that. And I feel that that gives me a lot of meaning for the day. But I feel that the pressures and the mechanism by which health care operates right now obfuscates that for so many people. And that’s sad to me. Now, I take a little bit of heart in that the medical field is really taking this seriously and is trying to do something about this. There is an added emphasis now on bringing in the arts and humanities into medicine.

Audio interview produced and edited by: Sam Briger and Thea Chaloner. Audio interview adapted for NPR.org by: Bridget Bentz, Molly Seavy-Nesper and Deborah Franklin.

Why Medicare politics are heating up : Shots

Why Medicare politics are heating up : Shots

Prescription drug coverage is just one particular portion of Medicare, the federal government’s health and fitness insurance policies software for folks age 65 and in excess of.

d3indicator/Getty Pictures


hide caption

toggle caption

d3signal/Getty Pictures


Prescription drug coverage is just one particular section of Medicare, the federal government’s wellbeing insurance coverage application for persons age 65 and over.

d3sign/Getty Illustrations or photos

The White Dwelling produced President Biden’s $6.8 trillion proposed budget very last week, listing his priorities for the approaching fiscal year. Among other things, Biden singled out Medicare — the federal wellness insurance program for people aged 65 or more mature. Republican leaders insist they is not going to be threatening cuts to Medicare in future price range negotiations, but other individuals in the get together have floated the thought of building modifications more than time to the system — including reward cuts they say will be important to preserve Medicare solvent.

NPR’s Michel Martin, as co-host of All Things Regarded as, sat down this 7 days with veteran health and fitness care journalist Julie Rovner, of Kaiser Wellness News, to get a superior feeling of where by the debate is headed above how to fund Medicare, an high-priced, but common system. The pursuing excerpt of their conversation has been edited for length and clarity.

MARTIN: So, what is the problem below?

ROVNER: Medicare’s trustees say that in six years, the trust fund is heading to run out of reserves, and so it is not going to be equipped to pay all of the recent gains. So generally, in get to deliver down the value, you have a few options: You can make the men and women who are on the program pay far more, you can make taxpayers who assist aid the method pay extra, or you can spend well being care providers — medical practitioners and hospitals and all these people — less.

Everybody considers any of people matters, “cuts,” despite the fact that shelling out suppliers considerably less is ordinarily only considered a slash to the providers. If the cuts get as well huge, and the well being treatment suppliers say “We are going to walk absent from the program,” which is a dilemma as well.

But Medicare is extremely well-liked, and I feel in the State of the Union, when the president mentioned he was not going to do anything at all to Medicare, people today type of slapped back and mentioned, “But Medicare is likely to go broke if we really don’t do everything.” So in the funds, Biden reported, nicely, listed here are a pair of issues that we could do, none of which affect how substantially beneficiaries spend.

MARTIN: What are the top rated strains of what President Biden’s proposing, in regards to Medicare?

ROVNER: It really is in fact relatively modest. Very last yr, for the initially time, Medicare was provided legal permission to negotiate the cost of medicine. There is a brief list of medicines. This budget would make the list more time, and it would have all those negotiations come about more rapidly. It would also raise a tax on quite superior-money earners — those earning about $400,000. The Biden finances would increase that Medicare tax from 3.8{515baef3fee8ea94d67a98a2b336e0215adf67d225b0e21a4f5c9b13e8fbd502} to 5{515baef3fee8ea94d67a98a2b336e0215adf67d225b0e21a4f5c9b13e8fbd502} on those higher earners.

MARTIN: Republicans have stated that they can balance the price range more than the subsequent decade, but won’t touch Medicare. Is that a credible stance?

ROVNER: It is, but only if they go right after Medicaid — the really bigger public wellbeing insurance system for men and women with lower incomes — and the subsidies on the Cost-effective Care Act, which the president has now also explained he will never go after. It is achievable to harmony the spending plan with no touching Medicare or Social Stability or raising taxes, but you would have to slice so a great deal from the relaxation of the funds. Which is why we have not seen a Republican strategy yet. They are continue to attempting to figure it out.

MARTIN: Senate Minority Chief Mitch McConnell has already explained publicly that Biden’s prepare to enhance the Medicare tax on significant earners, “will not see the gentle of day.” So what are we most likely to see next?

ROVNER: Well, at some position, you know, the two parties are going to have to come collectively before the Medicare trust fund runs out of revenue. This is not the initially time we’ve been inside this near interval the place the rely on fund could operate out of money. It is happened several periods in the previous. Inevitably, the parties do get jointly and figure out some way to shore it up. And I am positive that will come about this time, way too, but I suspect this yr is going to be far more of a combat primary up to the 2024 elections.

MARTIN: The talks about the debt ceiling are approaching. The leaders of both of those functions have claimed that Medicare is off the table. But is it conceivable that Medicare will not be implicated at some place in these talks?

ROVNER: No. Of system Medicare is likely to be implicated at some position in these talks. Initially of all, what Republican leaders say is not always what all of the Republican rank and file will do. That’s true of the Democrats, also, so it is really challenging to consider that Medicare would not be put on the desk in some way, shape or variety.

MARTIN: So, what will you be shelling out focus to as these conversations keep on around the up coming pair of months and months?

ROVNER: A thing demands to be done to Medicare, lest it run out of cash. So I believe that fairly considerably the overall federal panoply of health packages is going to be up for dialogue — and that is what I am going to be looking at.

MARTIN: I am just asking yourself, is this the type of subject that the general public genuinely can aim on, can actually get galvanized close to?

ROVNER: It can and it are unable to. The trick is how this receives negotiated and how it receives offered to the general public as to whether it will essentially impact their wellbeing care.

Julie Rovner is the Washington correspondent for KHN and host of “What The Wellbeing?” — KHN’s weekly well being coverage information podcast. Soon after almost 8 a long time of internet hosting Weekend All Issues Deemed, Michel Martin is having on a new hosting part on NPR’s Early morning Edition.